The T&O Portfolio Pathway: Your Route to the Specialist Register
What the GMC actually wants in your evidence bundle — broken down from the Specialty Specific Guidance for Trauma and Orthopaedic Surgery.
Unlike the CCT route, the Portfolio Pathway doesn’t track you through a training programme — it asks you to prove, in one go, that you already perform at day-one-consultant level. That means the evidence bar is high and very specific. Here’s what the GMC guidance actually asks for.
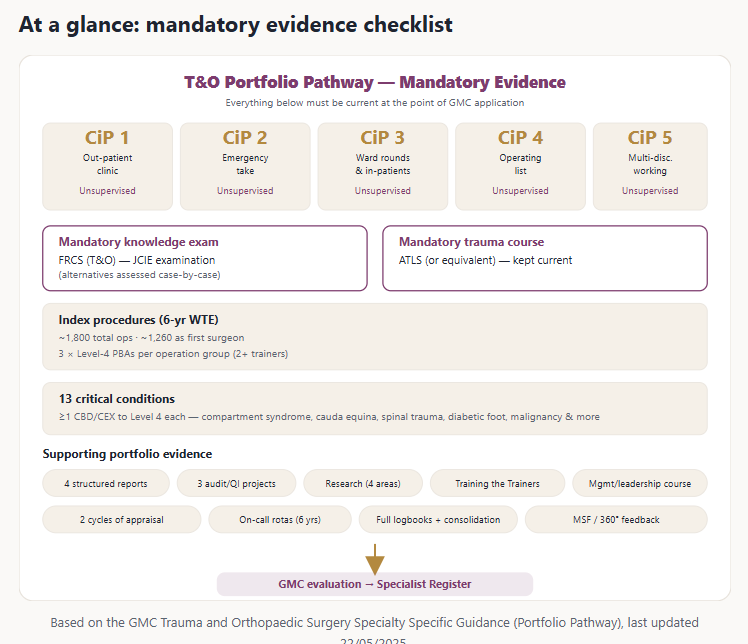
The five Capabilities in Practice you must evidence
Every surgical specialty shares the same five high-level outcomes. You need current evidence of unsupervised practice across all of them:
- CiP 1 — Manages an out-patient clinic
- CiP 2 — Manages the unselected emergency take
- CiP 3 — Manages ward rounds and in-patients
- CiP 4 — Manages an operating list
- CiP 5 — Manages multi-disciplinary working
Each one draws on the same underlying evidence: logbooks, WBAs, structured reports, CPD, research, teaching, audit, and management activity.
Currency of evidence matters more than volume
Evidence can be drawn from the last 6 years of clinical practice (whole-time equivalent, doesn’t need to be consecutive). But if you’ve had a break, at least half of your critical-condition CBDs and emergency index-procedure PBAs must come from your most recent 2 years of practice. A gap of 6 months or more right before you apply is a red flag the GMC actively tells applicants to fix before submitting.
The mandatory knowledge exam: FRCS (T&O)
The GMC is blunt about this one: the FRCS (T&O), set by the Joint Committee on Intercollegiate Examinations, is the qualification that demonstrates specialist-level knowledge. Related exams — the Joint Surgical Colleges Fellowship Examination, overseas FRCS versions, or the European Board exam (FEBOT) — are explicitly flagged as not equivalent on their own, because their scope, case mix, and depth of testing differ. Without the FRCS (T&O), you’re looking at an extensive competency-mapping exercise instead — and it’s assessed case-by-case.
Index procedures & numbers
You need to show breadth as well as volume. The indicative minimums:
| Measure | Indicative number |
|---|---|
| Total operations (last 6 years, WTE) | ~1,800 |
| Cases as first surgeon | ~1,260 |
| Major joint arthroplasty | 80 |
| Arthroscopy (knee/shoulder/ankle/hip/wrist/elbow) | 50 |
| Plate fixation for fracture/arthrodesis | 40 |
| Compression hip screw (NOF fracture) | 40 |
| Hemiarthroplasty (NOF fracture) | 40 |
| Intramedullary nailing | 30 |
| Osteotomy / nerve compression procedures | 20 each |
| K-wire fixation | 20 |
| Tendon repair for trauma | 10 |
| Application of limb external fixator | 5 |
| Tension band wire | 5 |
| Children’s displaced supracondylar fracture | 5 |
For each specific operation group you need 3 PBAs at Level 4, signed off by two or more different trainers — except supracondylar fracture fixation and external fixator application, where 1 Level-4 PBA is acceptable (and one of those may be in simulation).
Critical conditions
These are the conditions where a missed diagnosis costs life or limb. You need at least one CBD or CEX to Level 4 for each:
- Compartment syndrome (any site)
- Neurovascular injuries (any site)
- Cauda equina syndrome
- Spinal trauma assessment, care & referral
- Spinal infections & complications of inflammatory spinal conditions
- Metastatic spinal compression
- The painful spine / painful hip in the child
- Physiological response to trauma
- Necrotising fasciitis
- Diabetic foot
- Primary and secondary musculoskeletal malignancy
- Major trauma resuscitation (CEX)
Structured reports and the rest of the portfolio
Beyond logbooks and WBAs, the GMC wants:
- 4 structured reports from consultants who’ve observed your practice over the last 2 years — at least 2 with current training involvement, and 1 from your head of department
- ATLS (or equivalent trauma course) kept current
- 3 audit or QI projects in the last 6 years, with at least one full cycle completed
- Research evidence across 4 areas: evidence-based practice, critical appraisal, research principles, and research governance/ethics
- ‘Training the Trainers’ course (or equivalent) plus evidence of teaching delivered and feedback received
- A management/leadership course, plus evidence of an actual leadership role (rota organisation, clinical/audit lead, committee chair, etc.)
- 2 cycles of recent appraisal, one within the last year
- On-call rotas covering each post held in the evidence window, to prove the volume of emergency work
Worth knowing: the GMC explicitly warns against “unbundling” — splitting one operation into multiple logbook entries. One patient equals one operation. Reviewers check for this.
The finish line
Most successful applications run to 800–1,000 pages of evidence, organised precisely to mirror the online application structure. There’s no ARCP here — a GMC evaluation panel reviews the whole bundle against the CiPs and GPCs in one pass, so the burden of proof sits entirely on how the evidence is assembled and cross-referenced.